The Drum · Weekly AI news, freeSubscribe →

Share
For the hundreds of thousands of people living with advanced heart failure, every mechanical pump option has come with a tradeoff. Magnetic levitation may finally offer a way to keep blood moving without destroying it.
Heart failure doesn't announce itself with drama. It creeps in as breathlessness on the stairs, swelling in the ankles, exhaustion that sleep doesn't fix. For millions of people, the heart simply can't pump hard enough anymore to keep the rest of the body supplied with oxygen-rich blood. When medication and lifestyle changes stop being enough, and a donor heart isn't available or isn't yet needed, doctors turn to mechanical help: a device called a ventricular assist device, or VAD, that takes over some of the heart's pumping work.
These devices have saved countless lives. But they've also come with a frustrating catch. Traditional VADs rely on spinning rotors or moving mechanical parts that touch bearings, and anywhere metal touches metal inside a blood vessel, you get friction, heat, and wear. Worse, those contact points can damage blood cells as they pass through, a process doctors call hemolysis. Damaged blood cells can trigger clotting, and clots in a device meant to keep someone alive can instead cause a stroke. It's a bit like running a car engine with sand in the oil: it keeps moving for a while, but something eventually gives.
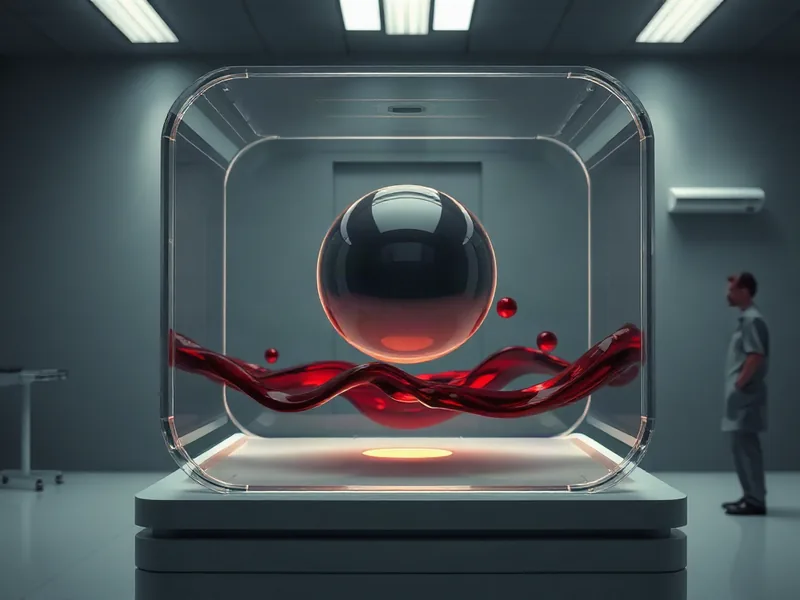
Engineers have been chasing a fix for years, and increasingly the answer looks like maglev, the same magnetic levitation principle that lets high-speed trains in Japan and China glide above their tracks without touching them. Instead of wheels on rails, powerful magnets keep the train suspended in midair, eliminating the friction that limits speed and causes wear. Apply that same idea to a heart pump, and you get a rotor that spins inside the device without ever touching its housing, levitated entirely by magnetic fields.
In a maglev heart pump, the impeller, the small rotating component that pushes blood forward, floats inside a chamber, suspended and controlled by magnets rather than resting on a physical bearing. Because there's no contact, there's no friction to generate heat, and no surface for blood cells to be sheared apart against. The pump can run continuously, for months or years, with dramatically less mechanical stress on the blood passing through it.
This matters enormously for patients who may rely on these devices not for weeks, but indefinitely, either as a bridge while waiting for a transplant or, increasingly, as what doctors call "destination therapy," a long-term solution in its own right. The longer a device needs to function inside someone's chest, the more any small source of wear or blood damage compounds over time. Removing the physical contact point doesn't just reduce the risk of catastrophic failure. It reduces the slow, cumulative harm that comes from a device subtly damaging the very fluid it's meant to protect.
Existing maglev-based ventricular assist devices have already reached patients, and engineers continue refining the magnetic control systems that keep the rotor precisely centered despite the body's own movements, blood pressure changes, and the pump's constantly shifting load. That control problem is harder than it sounds. A levitated train track is fixed and predictable. A human chest cavity is not. The magnetic system has to constantly sense and correct the rotor's position in real time, thousands of times per second, to keep it from drifting and touching the housing wall, all while the device sits inside a body that's walking, bending, sleeping, and breathing.
The engineering challenge is matched by a manufacturing one. These pumps need to be small enough to implant, durable enough to run nonstop for years, and reliable enough that a software or sensor glitch doesn't become a medical emergency. Every component, from the magnets to the control electronics to the battery and power transmission system, has to be miniaturized without sacrificing the precision that keeps the rotor safely suspended.
There's also the question of power. Levitating a rotor and running continuous sensing and correction takes energy, and that energy ultimately has to come from somewhere outside the body, usually through a cable or, in newer designs, through a system aimed at eventually enabling wireless transmission. For patients, that power connection is often the most visible and burdensome part of living with a VAD today: a cord that has to be managed, kept dry, and never allowed to fail. Reducing the energy demands of magnetic levitation, or finding more efficient ways to deliver that power, remains one of the field's open problems.
None of this is purely theoretical anymore. Maglev principles are already embedded in some of the heart pumps currently used in clinical practice, part of a broader generation of continuous-flow devices that have replaced older, bulkier pumps that mimicked the heart's natural pulsing action. The shift from pulsatile to continuous-flow, and now toward frictionless magnetic suspension, reflects a steady march toward devices that are smaller, quieter, and gentler on the body with each generation.
Heart failure affects an enormous and growing population worldwide, driven by aging demographics and rising rates of the conditions, like hypertension and diabetes, that damage the heart over time. Donor hearts remain scarce, and transplant waiting lists are long. For many patients, a mechanical pump isn't a stopgap; it's the only realistic option for staying alive long enough to see a transplant, or the permanent solution itself.
That reality raises the stakes on every engineering decision inside these devices. A pump that causes less blood damage means fewer strokes. A pump that lasts longer without mechanical failure means fewer repeat surgeries, each of which carries its own risks for an already fragile patient. And a pump that someday sheds its external power cord would mean a meaningful improvement in daily quality of life, letting people shower, dress, and move through the world with less fear of catastrophic equipment failure.
Maglev heart technology won't solve the organ donor shortage, and it won't replace the need for careful, individualized medical care. But as an engineering approach to one of medicine's hardest mechanical problems, keeping blood moving without damaging it, it represents a genuinely meaningful step forward, one grounded less in hype than in the same physics that already keeps trains gliding silently above their tracks.
Tags
Original Sources
This Maglev Heart Could Keep Cardiac Patients Alive
↗ https://spectrum.ieee.org/this-maglev-heart-could-keep-cardiac-patients-alive/particle-7
About the author
Amara's entry point into AI was an epidemiology role at a London research hospital, where she spent five years studying how digital health tools reached — or conspicuously failed to reach — underserved communities. Watching early algorithmic systems in healthcare quietly entrench existing inequalities, she redirected her career toward the systemic consequences of AI at scale. She covers AI through an unflinching lens: who benefits, who bears the cost, and what evidence actually says versus what the press release claims. Her writing is calm and precise, but she doesn't mistake balance for neutrality.
More from The Steward →This Week's Edition
18 October 2026
24 articles
Related Articles

How a Stubborn Hiss of Radio Noise Helped Confirm the Big Bang
Health & Science · 5 min
AI Can Predict Chemotherapy Response in Aggressive Breast Cancer, But Not Yet Reliably Enough for the Clinic
Health & Science · 5 min
xAI Launches Grok Bot, an Autonomous Agent That Logs Into Your Tools and Does the Work
Products & Applications · 5 min
Related Articles
How a Stubborn Hiss of Radio Noise Helped Confirm the Big Bang
Health & Science · 5 min
AI Can Predict Chemotherapy Response in Aggressive Breast Cancer, But Not Yet Reliably Enough for the Clinic
Health & Science · 5 min
xAI Launches Grok Bot, an Autonomous Agent That Logs Into Your Tools and Does the Work
Products & Applications · 5 min
More Stories
© 2026 Cedar & Bloom. All rights reserved.
